Author

Stephen J. Birchard DVM, MS, Diplomate ACVS

Saturday, September 12, 2015

Thyroid Cancer in Dogs: Not always a bad disease!

Thyroid neoplasia is fairly common in dogs and is seen more frequently in boxers, golden retrievers, and beagles.(1) The tumors are usually malignant and unilateral however bilateral tumors are possible. Carcinoma is the most common tumor and they can metastasize to lungs and regional lymph nodes.(2) They can also be locally invasive and spread into adjacent vasculature such as the jugular vein. Because of the complex nature of the cervical anatomy and potential invasiveness of thyroid tumors, surgical removal by a board certified veterinary surgeon is recommended.

Clinical Signs

Dogs may be minimally symptomatic and present for a mass in the neck that is either discovered by the owner or found on routine physical examination.(Fig. 1) 
Fig. 1: A West Highland White Terrier with a thyroid  tumor visible in the neck. (arrows)
If early diagnosis is pursued, the tumor may be small, encapsulated, and freely movable in the neck. More advanced tumors can be very large, fixed in position, and encompassing the trachea and larynx.

In rare cases the thyroid tumor is functional and secreting an excessive amount of thyroxine causing hyperthyroidism. Signs of hyperthyroidism include weight loss, increased appetite, polyuria and polydipsia. Cardiac abnormalities such as cardiomyopathy can result from the excessive thyroid hormone secretion. Submit blood samples for thyroid hormone panel to confirm the diagnosis of a functional thyroid tumor.

Diagnosis and Staging

An accurate preoperative diagnosis is important since masses in the neck other than thyroid tumors, such as those involving the salivary glands or lymph nodes, can occur. Carefully palpate the neck mass and regional lymph nodes. Small, well-circumscribed and freely movable tumors are usually amenable to surgical resection.

Fine-needle aspirate or tissue biopsy of the thyroid tumor helps establish the type of tumor. However, recognize that bleeding associated with these procedures can obscure the surgical field and make the procedure more difficult. Ultrasound examination may be helpful to identify the involved thyroid lobes, evaluate for local tissue invasion, and guide fine needle aspiration. Obtain thoracic radiographs to rule out pulmonary metastasis or other cardiopulmonary disorders.

Surgical Procedure

The objectives of surgery are to: completely remove the thyroid mass, preserve at least one parathyroid gland, minimize blood loss, and avoid injury to the recurrent laryngeal nerves, trachea, and esophagus.

Anatomy

The thyroid gland in the dog is divided into 2 lobes that are located adjacent to the trachea and just distal to the larynx.(3) (Fig. 2) 
Fig. 2: Normal anatomy of the cervical region in the dog. Arrows delineate the thyroid lobes.
(Illustration by Mr. Tim Vogt, Medical Illustrator, College of Veterinary Medicine, The Ohio State University)
The normal gland has a pale brown color and is approximately 2 to 2 and 1/2 cm in length.  The principle blood supply to each lobe is the cranial and caudal thyroid arteries, branches of the common carotid artery.  Venous drainage of the thyroid is via the cranial and caudal thyroid veins.

The thyroid gland has a distinct capsule that can be bluntly separated from the parenchyma.  Small blood vessels may be located on the capsule surface and between the capsule and the parenchyma of the gland. Two parathyroid glands are usually associated with each thyroid lobe.  The external parathyroid gland usually lies in the fascia at the cranial pole of the thyroid lobe.  The internal parathyroid gland is usually embedded in the thyroid parenchyma and is variable in location.  The external parathyroid glands are much smaller than the thyroid lobe and can be distinguished from the thyroid tissue by their lighter color and spherical shape. However, the parathyroid gland can be confused with fat.  The blood supply to the parathyroid glands also arises from the cranial thyroid artery.

Overview of Surgical Technique

The dog is placed in dorsal recumbency and the ventral cervical area prepared for aseptic surgery. A ventral midline cervical surgical approach is made from the larynx to the manubrium. The paired sternohyoideus muscles are divided on the midline and retracted. (Fig. 3) A stomach tube or small endotracheal tube in the esophagus helps identify this structure.
Fig. 3: Operative photograph of a unilateral thyroid tumor (arrows)
in a dog with thyroid carcinoma.
Ligate or cauterize the extensive vascular network surrounding the thyroid and carefully dissect out the tumor. Begin dissection at the caudal aspect of the tumor and gradually work cranially. (Fig. 4) 
Fig. 4: Dissection of a thyroid carcinoma in a dog proceeding from
caudal to cranial (black arrow). Yellow arrows indicate the trachea.
Identify the recurrent laryngeal nerves adjacent to the trachea and avoid trauma to them. If possible, identify and preserve the parathyroid glands especially with bilateral thyroidectomy. With large malignant tumors, the parathyroid glands may be difficult to indentify.

Close the muscle routinely with simple continuous, absorbable suture; the subcutaneous tissue with simple continuous, absorbable suture; and the skin with simple interrupted, nonabsorbable suture or an intradermal pattern using absorbable suture.

Postoperative Care and Complications

Short-Term

Closely monitor for hemorrhage or seroma formation at the surgical site. Cold compresses on the incision for the first 24 hours are helpful to prevent swelling.Monitor serum calcium concentrations for at least 2–4 days postoperatively if a bilateral thyroidectomy was performed. Monitor the calcium concentrations longer if the levels are decreasing. Treat hypocalcemia with oral calcium and vitamin D. If bilateral thryoidectomy was performed, evaluate thyroid function and treat hypoparathyroidism if necessary.

Long-Term

Reevaluate the dog frequently (every 3 months for the first year) with physical examinations and thoracic radiographs to monitor for recurrence of the primary tumor and metastasis.
Consider postoperative chemotherapy or radiation therapy if the tumor was malignant and incompletely excised.


Prognosis

Key Point:  Surgical resection of encapsulated, movable thyroid tumor in dogs has been found to result in median postoperative survival of 20 months.

In the study cited above the dogs were treated with surgery alone and had no evidence of metastasis at the time of surgery.(4) As with most cancers, early diagnosis and treatment increases the chances of a good outcome.

References
  1. Birchard SJ, Roesel OF: Neoplasia of the thyroid gland in the dog: A retrospective study of 16 cases. JAAHA 17:369-372, 1981.
  2. Brodey TS, Kelly DF: Thyroid neoplasms in the dog. Cancer 22: 406-416, 1968.
  3. Evans HE, Christensen GC: Miller's Anatomy of the Dog, The Endocrine System, WB Saunders, Philadelphia, 1979, pp. 611-618.
  4. Klein MK1, Powers BE, Withrow SJ, Curtis CR, Straw RC, Ogilvie GK, Dickinson KL, Cooper MF, Baier M. Treatment of thyroid carcinoma in dogs by surgical resection alone: 20 cases (1981-1989).J Am Vet Med Assoc. 1995 Apr 1;206(7):1007-9.

Friday, July 17, 2015

Does Spay or Neuter Make Dogs Overweight?


Effect of age at gonadectomy on the probability of dogs becoming overweight.

J Am Vet Med Assoc. 2013 Jul 15;243(2):236-43.

Summary

The authors of the above study compared 1,930 dogs that were spayed or neutered (gonadectomy) to 1,669 sexually in tact dogs to evaluate the tendency of the spayed or neutered dogs to become overweight.  They also looked at the effect of age at the time of gonadectomy to see if that had an effect on becoming overweight. All dogs were patients at Banfield Pet Hospitals, giving the authors a consistent data retrieval system. Follow-up on all animals was for a period of greater than or equal to 10 years.

The authors found that spayed or neutered dogs were statistically more likely to become overweight compared to sexually in tact dogs.  However, this was found only for the first 2 years after the spay or neuter. Age at gonadectomy and sex of the dog did not affect the tendency to become overweight.

An additional interesting finding in the study was that both groups of dogs (gonadectomy vs. sexually in tact) had a surprisingly high percentage of overweight individuals. In the sexually in tact dogs, 37% became overweight over time, and in the gonadectomized dogs, 66% became overweight. Also, large breed dogs were more likely to become overweight in this study.

Commentary

This was a well-designed and executed study of a large population of dogs. The diagnosis of being overweight seemed arbitrary since no objective criteria were used other than body condition scores, but veterinarians performing routine examinations of the dogs were the ones making the overweight diagnosis.

Looking at the entire group of dogs (3,599), over half of them were diagnosed as being overweight. Beyond the effect of gonadectomy, this study illustrates the larger problem of obesity in pets. Whether being fed too much, or exercising too little, a high proportion of pets in the US are at an unhealthy weight which is likely affecting their quality of life and resulting in secondary health problems. More research is needed to investigate the causes of obesity in pets and how it can be effectively managed.

What are your thoughts about this study and about the more global problem of pet obesity? Post comments either here or on facebook (Dr. Stephen Birchard, Veterinary Continuing Education).


Wednesday, June 10, 2015

Total Ear Canal Ablation in Dogs and Cats: A big surgery with big benefits.

Total ear canal ablation is removal of the entire ear canal. Indications for TECA include severe chronic otitis with obstruction of the canal, ear canal or middle ear neoplasia, severe trauma to the ear canal, or congenital abnormality that causes obstruction of the canal.

Key Point: Chronic proliferative otitis can result in calcification of the ear canal. This is an irreversible, end stage change in the ear that can only be resolved by TECA.

TECA is combined with a lateral bulla osteotomy (BO) to remove residual epithelium and debris from the middle ear after the ear canal is removed. Because of the prevalence of severe ear canal disease in dogs and cats, TECA/BO has become a common surgical procedure. However, a properly performed TECA/BO is a difficult procedure and can be associated with many complications. It should be performed by a board certified surgeon who is familiar with the anatomy of the ear and the technical aspects of the procedure. However, a well performed TECA can significantly improve quality of life of animals with ear disease.

Anatomy
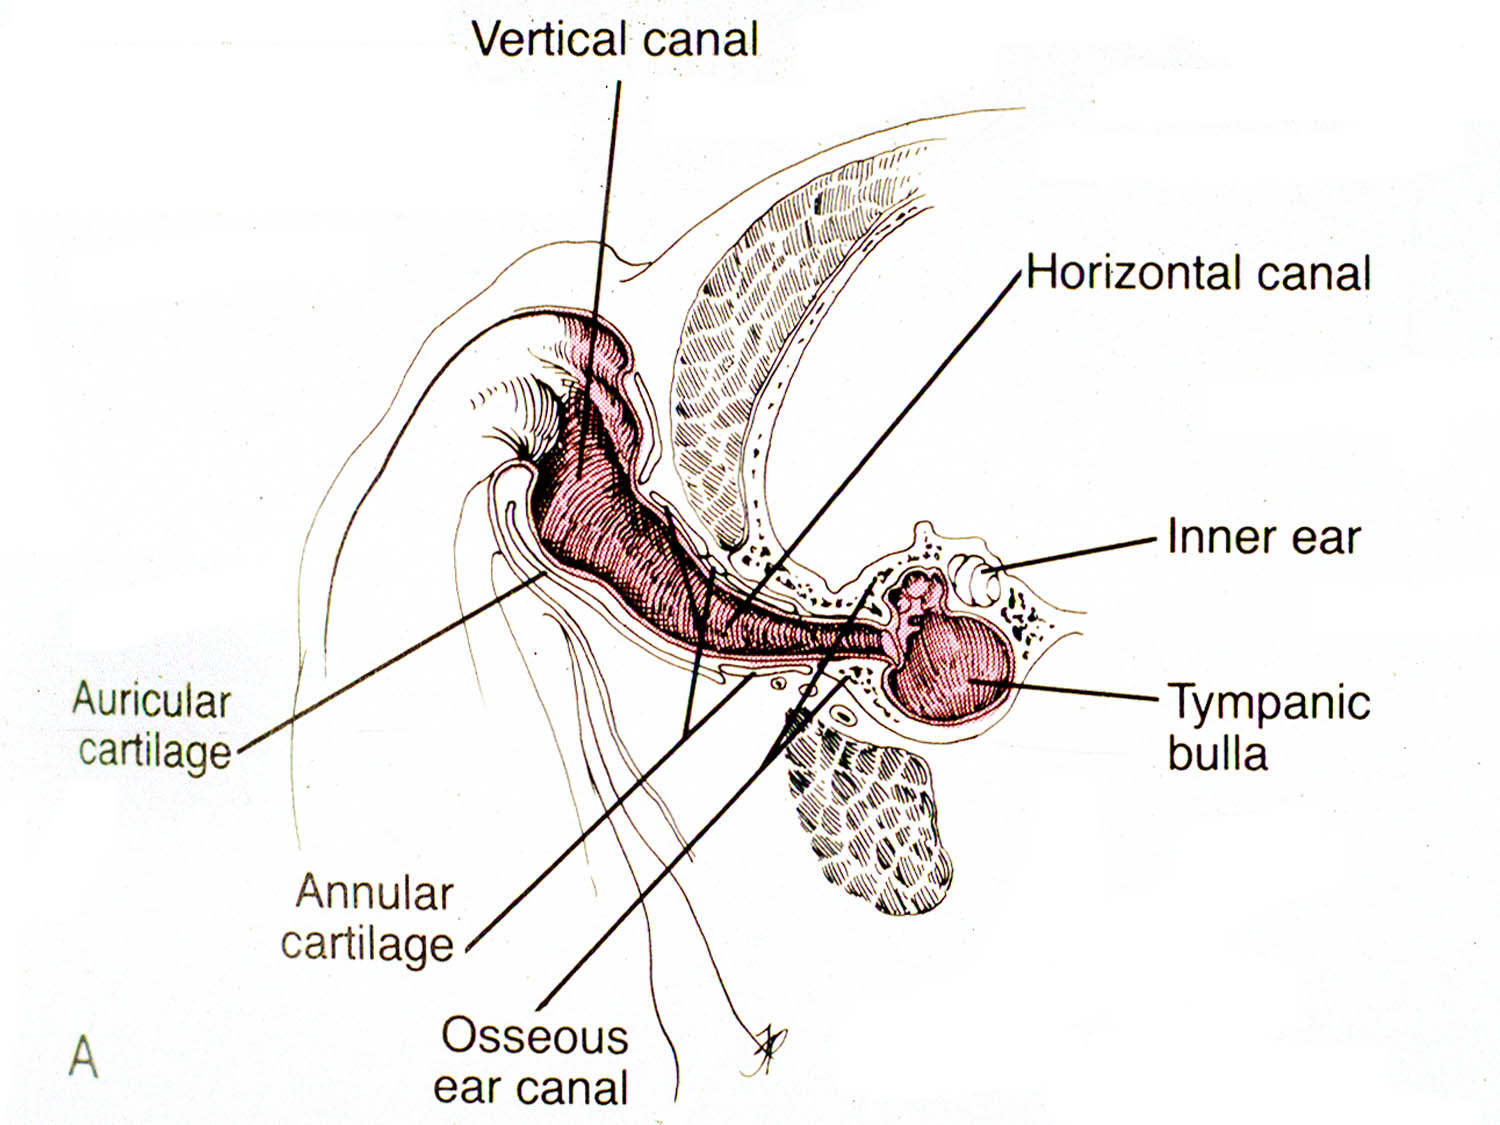
The entrance of ear canal, the external acoustic meatus, is surrounded by several cartilaginous structures including the tragus, antitragus, helix, and antihelix. The external ear canal in dogs and cats is divided into vertical and horizontal portions. (Fig. 1) 
Fig 1: Cross section of the ear canal in a dog.
(from: Smeak DD. Surgery of the ear canal and pinna. Saunders Manual of Small Animal Practice, 3rd ed., 
Birchard and Sherding editors, Elsevier, 2006)
The auricular cartilage is the vertical portion of the canal. The annular cartilage is located where the vertical canal turns into the horizontal canal. (Fig. 1)

The epidermal lining of the ear canal is rich in sebaceous and apocrine glands. In dogs with chronic otitis externa, an epithelial pouch may develop just adjacent and ventral to the tympanic bulla. (Fig. 2) 
Fig 2: Cross section of the ear in a dog with chronic otitis. Note the epithelial pouch
that develops in the canal adjacent to the entrance to the tympanic bulla. The tissue
colored red indicates that removed during a TECA/BO
(from: Smeak DD. Surgery of the ear canal and pinna. Saunders Manual of Small Animal Practice, 3rd ed.,
Birchard and Sherding editors, Elsevier, 2006)
The V-shaped parotid salivary gland lies over the ventro-lateral aspect of the vertical ear canal.

The middle ear is located in the petrous temporal bone. (Fig. 2) The tympanic bulla is the ventral wall of the tympanic cavity. It is an air-filled cavity just medial to the tympanic membrane. In the cat a septum divides the bulla into dorsomedial and ventrolateral compartments. Sympathetic nerve fibers run through the middle ear, and adjacent to the tympanic bulla are the facial nerve ventrolaterally, the carotid artery medially, and the hypoglossal nerve ventrally.

The major blood supply to the ear is via the great auricular artery and vein. Another important regional structure is the facial nerve. The nerve exits the skull just caudal to the ear canal and courses ventrally below the canal, then cranially. (Fig. 3) 
Fig. 3: Anatomy of important structures associated with the ear canal.
(from: Smeak DD. Surgery of the ear canal and pinna. Saunders Manual of Small Animal Practice, 3rd ed.,
Birchard and Sherding editors, Elsevier, 2006)
The nerve is motor to the lips and eyelids, therefore trauma to it causes lip droop and inability to blink.

Preoperative Considerations
Besides routine preoperative diagnostics such as history, physical examination, and blood tests, a good otoscopic exam and diagnostic imaging should be obtained on animals being considered for ear canal ablation.  Foreign bodies, neoplasia, or obstructive disorders of the canal may be discovered on otoscopic exam. Animals with tumors should also be screened for metastatic disease with thoracic radiographs, fine needle aspirate of regional lymph nodes if enlarged, and other tests as indicated. Skull radiographs or CT scan is usually recommended before TECA/BO to assess the tympanic bulla. See Veterinary Key Points blog “Nasopharyngeal Polyps in Cats”, 4/15/2015 for more discussion of bulla imaging techniques.

Surgical Procedure                      
After making the initial incisions around the external acoustic meatus and then ventrally along the vertical canal, carefully dissect the ear canal from surrounding tissues. (Fig. 4)
Fig. 4: Initial dissection in a canine cadaver for a TECA/BO. (note: Figures 4,5,7, and 8 are cadaver specimens.
 The cartilage around the external acoustic meatus has been severed 
and lifted up to allow dissection down the canal.
Dissect soft tissues close to the canal to avoid trauma to important structures, such as the facial nerve. (Fig. 5) 
Fig. 5: Continued dissection of the canal exposing the facial nerve in the stay suture. (arrow)
In ossified canals the facial nerve may be imbedded in the outer layer of the ear canal. (Fig. 6)
Fig. 6: The facial nerve (surrounded by yellow vessel loops) is being released from its adherence
to the ossified ear canal (arrow). Note the groove left in the canal by the nerve after gently dissecting it off.
 After removal of the canal using scalpel or scissors, carefully remove any remnants of canal and epithelium from the typanic bulla. Perform a bulla osteotomy with rongeurs to better expose the interior of the bulla. (Fig. 7) 
Fig. 7: After removal of the canal, the tympanic bulla is exposed by removing some of the
lateral aspect of the bony wall with rongeurs. Any remnants of the ear canal attached to the bulla
can also be removed with the rongeurs
Use a bone curette to remove epithelium and debris from the interior of the tympanic bulla. (Fig. 8) 
Fig. 8: Curettage of the interior of the bulla with a bone curette.
Avoid curettage of the dorsal aspect of the bulla to prevent trauma to the structures of the inner ear. Submit samples of fluid or debris from the tympanic bulla for culture and sensitivity. Also, submit the ear canal for histopathology to rule out neoplasia. Flush the incision with warm, sterile saline prior to closure. Close the incision in a “T” shape in multiple layers: deep fascia, subcutaneous tissue, and skin.

Postoperative Care and Complications
Postoperatively, protect the incision with a light bandage or Elizabethan collar. Administer analgesics for at least 3-5 days postoperatively. Long-term antibiotics (i.e. 3-4 weeks) are indicated in animals with bacterial infections. Choose antibiotics based upon the results of culture and sensitivity. If the animal’s eyelid motor function is decreased due to facial nerve injury, keep the eye lubricated with eye ointments or drops (e.g. Duratears) administered every 4-6 hours to prevent corneal ulcers until facial nerve function returns. 

Complications of TECA include acute pharyngeal edema, facial nerve damage, wound infection or dehiscence, Horner's syndrome, or deep abscesses. Deep abscesses occur due to leaving small amounts of secretory epithelium in or around the tympanic bulla. Reoperation to retrieve the residual epithelial tissue is usually necessary. Depending on the study, facial nerve deficits after TECA/BO in dogs can range from 36 to 48%, and in cats as high as 56%.(1-3) Although hearing is certainly diminished, some studies have found that some ability to hear is preserved even after removal of the ear canal.(2)

References
1. DD Smeak, WD DeHoff. Total Ear Canal Ablation Clinical Results in the Dog and Cat. Veterinary Surgery Volume 15, Issue 2, pages 161–170, March 1986
2. R. A. S. White, C. J. Pomeroy. Total ear canal ablation and lateral bulla osteotomy in the dog  Journal of Small Animal Practice Volume 31, Issue 11, pages 547–553, November 1990
3. Rebecca E. Spivack, A. Derrell Elkins, George E. Moore, and Gary C. Lantz (2013) Postoperative Complications Following TECA-LBO in the Dog and Cat. Journal of the American Animal Hospital Association: May/June 2013, Vol. 49, No. 3, pp. 160-168

Tuesday, April 21, 2015

Is Tramadol An Effective Postoperative Analgesic in Dogs?


Postoperative pain control is a critical aspect of the care of surgical patients in veterinary medicine. Many drug types are available for postoperative analgesia such as opioids and non-steroidal antiinflammatories. Tramadol, a synthetic opioid, is a widely used analgesic in humans and has become popular for clinical use in dogs. It is an oral medication usually given at a dose of 2-4 mg/kg every 8-12 hours. It is frequently combined with a non-steroidal anti-inflammatory, such as carprofen, for postoperative analgesia. Side effects of tramadol include sedation, nausea, constipation, and seizures. Tramadol therefore is not recommended for dogs with seizure disorders.

Metabolism
Tramadol is metabolized by the liver to form O-desmethyltramadol, or the M1 metabolite.(1) This metabolite is also an active form of the drug. Pharmacokinetic studies have found that oral administration of tramadol results in adequate blood levels of the drug and its metabolite.(1)

Efficacy
Although rapidly gaining widespread use after introduction to the veterinary market, efficacy studies of the analgesic properties of tramadol have been slow to materialize. One study from several years ago separately evaluated morphine and tramadol for postoperative analgesia after ovariohysterectomy in dogs.(2) Using multiple parameters to evaluate pain, both drugs were found to be effective.  In another study, tramadol was compared to codeine and ketoprofen for analgesia after maxillectomy or mandibulectomy in dogs.(3) All drugs, including tramadol, were found to provide effective postoperative analgesia.

Conversely, more recent studies have found tramadol to compare poorly to other standard analgesics for postoperative pain. Carprofen was more effective than tramadol for postoperative pain in a series of dogs having enucleation.(4) Pain scores were monitored and dogs receiving tramadol were more likely to require rescue analgesics than those receiving carprofen. In another study, after TPLO for ruptured cruciate in 30 dogs, those that received firocoxib orally, alone or in combination with tramadol, had lower pain scores, lower rescue opiate administration, and greater limb function than dogs that received only tramadol.(5) Tramadol was also not effective in providing analgesia in an experimental study using an acute pain model in Beagles.(6)

These studies create a mixed and confusing message to veterinary clinicians about the efficacy of tramadol. Inherent to all pain studies is the difficulty in making objective assessments of postoperative pain in dogs, but well controlled studies using accepted methods of pain scoring should provide useful information. The conflicting results of clinical and experimental studies make it clear that tramadol alone as a postoperative analgesic may not provide the expected level of analgesia. This appears to be particularly true after procedures associated with high pain levels, such as in dogs having major orthopedic surgery.

Conclusions
Even in view of the studies showing lack of efficacy, tramadol’s advantages make it an attractive choice for postoperative analgesia. It is administered orally, is well tolerated by most dogs, and is felt by many clinicians to be a reasonable alternative for dogs in which NSAIDS are contraindicated. We routinely use tramadol in combination with carprofen for postoperative analgesia in dogs. In our clinical experience that combination provides effective analgesia even after orthopedic procedures such as TPLO. Tramadol alone is prescribed in those dogs that cannot take NSAIDS since there are few alternatives and tramadol is certainly better than no analgesic treatment.

What is your clinical expertience with Tramadol? Go to the 1 question survey on the web version of the Veterinary Key Points blog and register your vote! 

References
1. KuKanich, B. and Papich, M. G. (2004), Pharmacokinetics of tramadol and the metabolite O- desmethyltramadol in dogs. Journal of Veterinary Pharmacology and Therapeutics, 27: 239–246.

2. Mastrocinque, S. and Fantoni, D. T. (2003), A comparison of preoperative tramadol and morphine for the control of early postoperative pain in canine ovariohysterectomy. Veterinary Anaesthesia and Analgesia, 30: 220–228.

3. Martins TL1, Kahvegian MA, Noel-Morgan J, Leon-Román MA, Otsuki DA, Fantoni DT.
Comparison of the effects of tramadol, codeine, and ketoprofen alone or in combination on postoperative pain and on concentrations of blood glucose, serum cortisol, and serum interleukin-6 in dogs undergoing maxillectomy or mandibulectomy. Am J Vet Res. 2010 Sep;71(9):1019-26.

4. Cherlene Delgado, DVM, Ellison Bentley, DVM, DAVCO, Scott Hetzel, MS, and Lesley J Smith, DVM, DACVAA. Carprofen provides better post-operative analgesia than tramadol in dogs after enucleation: A randomized, masked clinical trial. J Am Vet Med Assoc. 2014 December 15; 245(12): 1375–1381.

5. Davila D1, Keeshen TP, Evans RB, Conzemius MG.
Comparison of the analgesic efficacy of perioperative firocoxib and tramadol
administration in dogs undergoing tibial plateau leveling osteotomy. J Am Vet Med Assoc. 2013 Jul 15;243(2):225-31.

6. Kogel B, Terlinden R, Schneider J. Characterisation of tramadol, morphine and tapentadol in an acute pain model in Beagle dogs. Vet Anaesth Analg. 2014 May;41(3):297-304


Sunday, April 12, 2015

Nasopharyngeal Polyps in Cats: Key words - stertor, traction, and bulla osteotomy

Nasopharyngeal (NP) polyps in cats are characterized by well-circumscribed solid masses that are found in the nasopharynx, tympanic bulla, and Eustachian tube.  They are benign and thought to be secondary to inflammation from bacterial or viral infections.  Similar polyps can also be present in the external ear canal.  Affected cats are usually young (less than 1 year) but all ages can be affected.

Clinical Signs

Presenting signs of nasopharyngeal polyps may vary depending on location. Inspiratory stertor is commonly found due to the fleshy mass just dorsal to the soft palate causing obstruction of the nasal passages. Stertorous breathing in cats should alert the clinician to a mass lesion in the nasopharynx since other causes, such as elongated soft palate, are uncommon in cats.

Signs of otitis media, such as Horner’s syndrome, head tilt, and pain may also be seen. (Fig. 1) 
Fig. 1: Right sided Horner's syndrome seen in a kitten with a
NP polyp. 
Polyps in the external ear canal can result in or be secondary to otitis externa causing head shaking, ear scratching, and malodorous otic discharge.

Diagnosis

A thorough oral examination should be performed. Sedation will probably be necessary since the polyp will likely be obscured by the soft palate. If the mass is large enough simple palpation of the soft palate with a finger may indicate a mass effect. Retraction of the soft palate with stay sutures or a spay hook, with the cat in dorsal recumbency, should expose the mass. (Fig. 2)
Fig. 2: NP polyp in a cat (arrow) adjacent to the soft palate (SP) The cat is in
dorsal recumbency.

Otoscopic examination should also be performed to look for extensions of polyps into the external ear canal. Cleaning of otic discharge and debris may be necessary to adequately expose the mass.

Differential diagnoses for nasopharyngeal polyps are lymphosarcoma, other types of  neoplasia, foreign body, or congenital anomaly of the pharynx or upper airway. In one study of nasopharyngeal disorders in 53 cats 49% of them were diagnosed with lymphosarcoma and  28% were diagnosed as polyps.(1)

Imaging

Skull radiographs with emphasis on the tympanic bulla may provide useful information. Affected cats may show radiographic signs of chronic otitis media such as bony proliferation of the bulla and increased soft tissue density within the bulla.(Fig. 3)
Fig. 3: Bony proliferation of the bulla (arrow) secondary to
a nasopharyngeal polyp in a cat.
However, radiographs of the bullae are not a very sensitive imaging test and significant changes may be present with normal appearing bullae on films.

CT scans are a more sensitive and diagnostic imaging modality for bulla disorders and are useful in cats with nasopharyngeal polyps or other bulla diseases. Increased soft tissue density is commonly seen in one or both bullae. (Fig. 4)
Fig. 4: CT scan of a cat with a NP polyp showing increased soft tissue density
within the bulla. (arrow)
In cases of severe infection or invasive neoplasia, lysis of the bulla may be seen. These findings are useful for preoperative evaluation of cats undergoing ventral bulla osteotomy, a recommended surgery for cats with nasopharyngeal polyps or other chronic middle or external ear disease.

Treatment

Traction

Surgical removal of the polyps is the most effective means of relieving clinical signs. Under general anesthesia the cat is placed in dorsal recumbency and a mouth speculum placed to allow exposure of the oral cavity and pharynx. The soft palate is retracted rostrally with either stay sutures or a spay hook. Gentle manipulation of this tissue is important since it is sensitive and prone to edema with manipulation.  Even under anesthesia many cats will exhibit discomfort while the soft palate is being manipulated. Once the polyp is exposed, grasp it with either stay sutures or Allis tissue forceps.(Fig. 5) Gentle but firm rostral and ventral traction is placed on the polyp and continued until the mass is removed. 
Fig. 5: NP polyp (arrow) being removed by traction.
The tissue frequently has a large round component that is connected to a tail that is the Eustachian tube portion of the polyp. Control hemorrhage with direct pressure on the affected pharyngeal tissues.

Bulla Osteotomy

To completely remove the polyp tissues, ventral bulla osteotomy is then performed. Which side to operate depends on the preoperative imaging or lateralizing clinical signs. If lateralization was not possible or if changes are seen bilaterally on imaging, both bullae are ostetomized to be sure of removing all remaining polyp tissues. Although most polyps are unilateral, the author recently treated a cat with bilateral polyps requiring osteotomy of both bullae.

Small fragments of polyp tissue are usually found in the tympanic bullae exposed by the ventral bulla osteotomy. (Fig. 6-7)
Fig. 6: Diagram of a ventral bulla osteotomy in a cat. Rongeurs are used to
remove the ventral aspect of the bulla and expose both compartments.
from: Boothe H. Surgery for otitis media and otitis internal.
From: Saunders Manual of Small Animal Practice3rd ed., Birchard and Sherding, editors. Elsevier, 2006, pg. 601.

Fig. 7: Bulla osteotomy in a cat with NP polyps. The ventral floor of the
bulla has been removed. Note the polypoid tissue filling the bulla cavity. (arrow)

It is important to expose both compartments of the bulla when performing the osteotomy (ventral-medial and dorso-lateral chambers). Care is taken not to injure components of the inner ear, located dorsally in the bulla, when doing polyp excision and curretage.  Save all tissues removed for histopathology and obtain samples from the bulla for culture and sensitivity.

Postoperative Care and Complications

Routine supportive care including analgesics and antibiotics are administered postoperatively. Antibiotic choice is guided by results of culture and sensitivity of samples obtained from the bullae.

Common complications after polyp removal are pharyngeal swelling and Horner’s syndrome due to injury to sympathetic nerves in the middle ear. Both of these problems are usually mild, short term in duration, and not requiring treatment. Recurrence of polyps is more likely if only the nasopharyngeal portion is removed. In a clinical study of 31 cats with nasopharyngeal polyps, 5 recurred postoperatively, 4 of which did not have a bulla osteotomy. (2)

References

1. HS Allen, J Broussard, and K Noone (1999) Nasopharyngeal diseases in cats: a retrospective study of 53 cases (1991-1998). Journal of the American Animal Hospital Association: November/December 1999, Vol. 35, No. 6, pp. 457-461. 
2. Kapatkin, AS, Matthiesen, DT, Noone KE. et.al. Results of surgery and long-term follow-up in 31 cats with nasopharyngeal polyps. J Am An Hosp Assoc 1990 Vol 26 No 4 pp. 387-392.


Monday, March 9, 2015

Message to Massive Liver Tumors in Dogs: We are not afraid of you!

Tumors of the liver are frequently seen in dogs, with the most common being the hepatocellular carcinoma. Affected dogs present for non-specific clinical signs and the tumors can become very large before being discovered. Massive liver tumors are defined as large tumors that are confined to one lobe of the liver.(1) (Fig. 1) 

Fig. 1: Large hepatocellular carcinoma of the liver in a dog

Prior to availability of surgical stapling devices such as the Thoracoabdominal Stapler (TA), liver lobectomy was tedious, risky, and associated with significant blood loss. The stapling device has made removal of even very large hepatic tumors safer and much faster resulting is less morbidity and mortality. (Fig. 2)

Fig. 2: Large liver mass in a dog being removed using
an older version of the thoracoabdominal stapling device
Diagnosis
Dogs with liver tumors present with non-specific signs such as lethargy, anorexia, and weight loss. A large cranial abdominal mass is usually palpable on physical examination. Diagnostic imaging is indicated including plain film abdominal radiographs (Fig. 3), abdominal ultrasound, and thoracic radiographs to look for metastatic lesions.
Fig. 3: Plain film abdominal radiograph of a liver tumor in a 12 year old Labrador retriever (arrow)
(photo courtesy of Dr. Laura Lemmons)
CT scan can also be performed (Fig. 4), however it may not provide more significant information than radiographs and ultrasound.
Fig. 4: CT scan of a 10 year old golden doodle with a large right sided liver
mass.(arrow) The mass was surgically removed and histopathology revealed a hepatic adenoma.

Preoperative Care

Appropriate preoperative diagnostics are necessary to rule out metabolic diseases and metastasis of primary liver tumors.  Preoperative hemograms and coagulation status should be assessed since many liver and biliary diseases can cause deficiency of clotting factors.  Serum proteins should also be evaluated.  The patient's fluid and electrolyte status should be considered and abnormalities corrected before surgery.  Significant blood loss can occur during or after partial hepatectomy which may require blood tranfusion.


Applied Anatomy

The liver is divided into 6 lobes, the caudate, right lateral, right medial, quadrate, left lateral, and left medial. 
Fig. 5: Normal gross anatomy of the canine liver lobes.
The liver has a dual blood supply, receiving circulation from both the portal vein and the hepatic arteries.  Major hepatic portal vein branches are the right lateral trunk, right medial branch, and left lateral trunk supplying the left lobes.  The liver portal vasculature can also be classified as right divisional (caudate and right lateral), central divisional (right medial and quadrate), and left divisional (left medial and left lateral). Six to eight major hepatic veins drain into the caudal vena cava.  The liver is attached to other structures in the abdomen via the triangular ligaments and the hepatogastric and hepatoduodenal ligaments.


Surgical Approaches

The liver is best approached via a ventral midline celiotomy.  Although rarely done, a right or left paracostal incision can be combined with the midline approach for large liver masses or other conditions that require greater exposure.  Caudal ventral midline sternotomy can be combined with the midline abdominal incision if necessary for cranially located masses.


Partial hepatectomy

Liver lobectomy using surgical staples is the procedure of choice for most surgeons. Complete or partial lobectomy can be performed. Omental adhesions to the mass will require hemostasis and sharp dissection to release them from the tumor. The Ligasure or electrocautery device is useful for hemostasis. After exposing the mass, incise triangular ligaments as needed to mobilize the liver lobe. Be cautious working around the hepatoduodenal ligament since the hepatic arteries and common bile duct are in the region. Caudal traction on the liver lobe is necessary to accurately place the stapler proximal to the tumor. (Figs. 6,7)
Fig. 6: Surgical removal of a large hepatocellular carcinoma
in a dog using the Thoracoabdominal stapler. 
Large hemostatic clips may be needed to control occasional arterial bleeders that were not adequately compressed by the staples. The Ligasure device can also be used to control liver bleeding. 
Fig. 7: Liver mass in same dog as in Fig. 3; histopathology of the
mass revealed an hepatic adenoma.
The liver has a remarkable ability to regenerate. Up to 60-70% of the liver tissue mass can be removed without impacting liver function.


Postoperative Care and Complications

Liver surgery patients should be closely monitored and supported after liver surgery.  Postoperative hemorrhage is possible and should be monitored via the patient's color, heart rate, peripheral PCV (measured several hours after surgery), and evidence of bleeding from the incision or blood in the abdominal cavity.  Routine postoperative supportive care with intravenous fluids and analgesics is administered. In the absence of complications, most dogs can be discharged from the hospital the day after surgery.

Prognosis
The prognosis for dogs after removal of massive liver tumors, even hepatocellular carcinoma if completely excised, is very good. In one study of 42 dogs, mortality rate was only 4.8% and median postoperative survival was greater than 1460 days.(1)  In contrast, dogs treated without surgery had a median survival was 270 days.

References
1. Julius M. Liptak, BVSc, MvetClinStud; William S. Dernell, DVM, MS, DACVS; Eric Monnet, DVM, PhD, DACVS; Barbara E. Powers, DVM, PhD, DACVP; Annette M. Bachand, PhD; Juanita G. Kenney; Stephen J. Withrow, DVM, DACVS, DACVIM. Massive hepatocellular carcinoma in dogs:48 cases (1992–2002) JAVMA, Vol 225, No. 8, October 15, 2004